

Neuropsychologist Aarón Fernández explains neuropsychological assessment and neuropsychological rehabilitation in aphasias.
The role of neuropsychology in aphasias
Aphasias, defined as the set of language and communication impairments resulting from brain damage, limit the person’s life in ways that go far beyond the language problem itself.
Given this complexity, it is necessary to have a team made up of many professionals who, from different perspectives, try to help recover the greatest possible functionality and facilitate the person’s adaptation to their new life situation.
Speech therapists, occupational therapists, physiotherapists, social workers, clinical psychologists should provide their assessment, and, if necessary, their intervention options. Of course, the neuropsychologist also plays an important role in this whole process which we will try to outline in this article.
The neuropsychologist is responsible for describing the cognitive profile that the person presents after the brain injury that caused that aphasia. In this sense, when we understand language as a cognitive function, it is difficult to try to separate it from other functions on which it is based and which it also influences, such as working memory, executive function, memory, among others (1). Knowing this profile is key to understanding which resources we can and cannot rely on during rehabilitation.
Moreover, neuropsychology is one of the disciplines responsible for channeling the advances coming from neuroscience on how language itself works, which are opening up new ways of approaching rehabilitation: moving from a model of syndromic categories to an approach based on language processes (2,3).
Neuropsychological assessment of aphasias
The underlying model
One of the important requirements for the neuropsychological assessment of language is having a model that allows us to understand how it works.
It is common to resort to the classical Wernicke-Geschwind model (4) which proposes a series of closed and segmented syndromes, but which proves insufficient to describe the language impairments present in a person with aphasia, and, therefore, not specific enough to serve as the assessment basis for a subsequent rehabilitation program.
At two perfectly complementary levels we have some models that may be more useful to us.
At the anatomical-functional level, we have the dual-route model proposed by Hickok and Poeppel (5) which defines two routes related to linguistic production and language comprehension respectively.
A dorsal route (equivalent to the Wernicke-Geschwind model itself) related to aspects of phonological construction, grammar and articulatory control, and a ventral route more related to aspects of auditory comprehension, both the discrimination of verbal sounds, as well as semantic or grammatical aspects.
Subsequently, Friederici and Gierhan (6) added two subdivisions to those routes that attempt to separate several processes and associate them with different fasciculi.
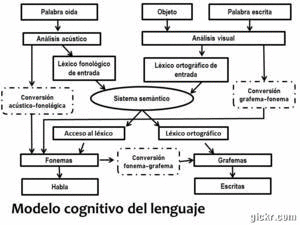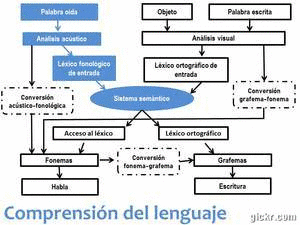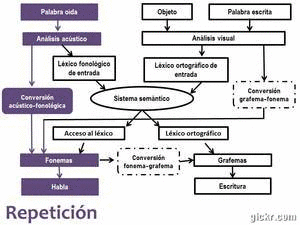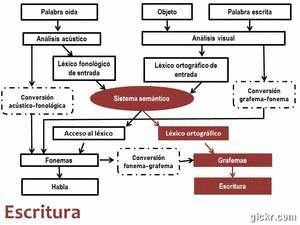
At a more purely cognitive level we have the language processing model proposed by Ellis and Young (7) that allows us to dissociate various processes within the different aspects of language that we have typically assessed, and, therefore, to more clearly discern the cause of the problem we observe. Knowing this model is essential for a correct approach to aphasias.
Some tests for the neuropsychological assessment of aphasias
Consequently, the key to designing a rehabilitation program lies in our ability to detect which language processes are impaired and which are not. To do so, it is essential to identify the different dissociations by administering specific tasks and analyzing the errors they produce.
Batteries that allow us to reach this level of analysis include, for example, the BETA battery and the EPLA battery (the Spanish adaptation of PALPA), which consist of different tasks that reveal the basic processes of language. The Pyramids and Palm Trees test is also useful for assessing the semantic component.
However, in most cases a broader assessment is also needed to determine how other cognitive functions may be affecting language in general or a particular process.
A note on what we leave out
It should not be forgotten that, in many cases, assessment is not just about locating the impaired process: it is also important to look at how that problem affects each person. And that is unique, so it could be said that each person really has a different type of aphasia, and only by paying attention to the person in front of us will we find the right approach.
The neurofunctional assessment tests we routinely use to measure the impact of brain damage on daily life are barely sensitive, if at all, to the impact that a language impairment has on our lives (8). It is recommended to use specific tests such as the Communicative Effectiveness Index (CETI), the CADL-2 (Communication Activities of Daily Living) or the Communicative Activity Log (CAL).
Neuropsychological Rehabilitation of Language
Approach to aphasia rehabilitation
Starting from these premises, our neuropsychological approach must be centered on working with the processes that we find altered after our prior assessment.
These can be rehabilitated using classical techniques such as errorless learning or by associating different elements with linguistic output (for example, associating elements of a sentence and their order with colors to work on agrammatisms). What follows from this is that each treatment will be specific and very different for each person.
Still, the REGIA program is noteworthy: it applies the constraint-induced approach used with the unaffected limb in motor rehabilitation to the language domain, in this case by restricting non-verbal communication. It is an intensive group treatment with good scientific evidence supporting its use (9).
Another important key is the use of alternative communication systems, to compensate for the person’s more severe language difficulties.
It should not be forgotten that, after an aphasia, the person ends up needing a complete adaptation to their environment and to understand the world in a new way (10), so the intervention should not be confined to the therapy room.
In the chronic phase
Finally, it should be stated that neuropsychological treatment in aphasias has been shown to be very effective in the year following the injury, but also when we enter the chronic phase, as there is evidence supporting the benefits of continuing treatment in chronic patients (9).
Bibliography
- Cahana-Amitay D, Albert M. Redefining Recovery from Aphasia. Oxford, New York: Oxford University Press; 2015. 296 p.
- Tremblay P, Dick AS. Broca and Wernicke are dead, or moving past the classic model of language neurobiology. Brain Lang. November 1, 2016;162:60-71.
- Vega FC. Neuroscience of Language: Neurological Bases and Clinical Implications [Internet]. Madrid: Panamericana; 2011 [accessed March 7, 2018]. Available at: https://dialnet.unirioja.es/servlet/libro?codigo=555469
- Geschwind N. Disconnexion syndromes in animals and man. I. Brain J Neurol. June 1965;88(2):237-94.
- Hickok G, Poeppel D. Dorsal and ventral streams: a framework for understanding aspects of the functional anatomy of language. Cognition. June 2004;92(1-2):67-99.
- Friederici AD, Gierhan SM. The language network. Curr Opin Neurobiol. April 1, 2013;23(2):250-4.
- Ellis AW, Young AW. Human Cognitive Neuropsychology: A Textbook With Readings. Psychology Press; 2013. 694 p.
- Terradillos E, López-Higes R. Guide to speech therapy intervention in aphasias. 2016.
- Berthier ML, Green C, Lara JP, Higueras C, Barbancho MA, Dávila G, et al. Memantine and constraint-induced aphasia therapy in chronic poststroke aphasia. Ann Neurol. May 2009;65(5):577-85.
- Paniagua PJ. The environment as a communication system [Internet]. Logocerebral. 2018 [accessed March 7, 2018]. Available at: http://logocerebral.es/entorno-sistema-comunicacion/
If you liked this post about aphasias, you may be interested in these NeuronUP posts:





“This article has been translated. Link to the original article in Spanish:”
Evaluación y rehabilitación neuropsicológica en las afasias

 Celebrities contribute to normalizing mental health issues

Leave a Reply