

In this article, neuropsychologist Ramón Fernández de Bobadilla explains how to carry out neuropsychological rehabilitation in Parkinson’s disease.
What is Parkinson’s disease?
Parkinson’s disease is the most common motor neurodegenerative disorder, with an estimated prevalence in Europe of 108–207 per 100,000 people. Although a minority of cases have a genetic origin, the cause is largely unknown, and age is the main risk factor for developing it.
The disease progresses very slowly, and many of its symptoms are caused by the death of dopaminergic neurons and the resulting decrease in terminals related to this neurotransmitter.
Symptoms of Parkinson’s disease
The four diagnostic pillars of Parkinson’s disease are:
- bradykinesia,
- rigidity,
- tremor,
- postural instability.
Symptoms typically appear on one side of the body and, although they become bilateral over time, the asymmetry usually remains. Although the symptom most commonly associated with Parkinson’s disease by the public is tremor, it is in fact neither a defining nor a specific symptom. What really defines Parkinson’s disease is parkinsonism. This necessarily involves bradykinesia (fewer and slower voluntary movements, which become evident on examination through impaired repetitive movements).
Initial phase
After motor symptoms appear, patients go through an initial phase with a good response to drug therapy through dopamine replacement, which usually lasts about 5 years.
Progression
From then on, complications gradually develop and new symptoms appear as neurodegeneration progresses. The time from the onset of motor symptoms to disability varies greatly between patients and generally ranges from 10 to 20 years.
Non-motor symptoms
Despite the importance of motor symptoms, more and more attention is being paid to the non-motor symptoms of Parkinson’s disease. This is not only useful for diagnosis (since they are present at all stages of the disease), but is also crucial for the follow-up and care of these patients because of their significant impact on quality of life.
Non-motor symptoms are highly complex and include both cognitive and neuropsychiatric aspects, as well as sleep disorders, autonomic dysfunction, and gastrointestinal or sensory symptoms. Some of these symptoms may be caused or worsened by dopaminergic medication itself (dopamine dysregulation syndrome, hallucinations, psychosis, orthostatic hypotension, daytime sleepiness, etc.).

Subscribe
to our
Newsletter
Cognitive impairment in Parkinson’s disease
Parkinson’s disease almost inevitably leads to cognitive impairment over its course, and up to 80% of patients develop dementia after 20 years. In the early stages, about 30% of patients have mild cognitive impairment, which is an independent risk factor for later developing dementia.
In addition to cognitive impairment, anxiety, depression, apathy, illusions, and hallucinations are very common in Parkinson’s disease.
Cognitive disorders are now recognized as highly prevalent symptoms that are vitally important to these patients’ quality of life.
Traditionally, they have been attributed to dopamine depletion secondary to neurodegeneration of the substantia nigra, which led to a deficit of this neurotransmitter in the striatum and, as a result, to the failure of frontal-subcortical circuits.
However, in recent years this view has broadened, given the growing evidence of the involvement of cortical and extranigral structures.

Speech-Language Pathology and Language Disorders in Parkinson’s
Parkinson’s disease is a neurodegenerative disorder that affects muscle movement and the central nervous system. Among the functions it affects, …
Neuropsychological profile in Parkinson’s disease
Early cognitive deficits in Parkinson’s disease may not be clinically apparent but can be detected through a formal neuropsychological assessment.
In this way, we can find cognitive deficits in patients who appear unaffected, and most of these deficits are dysexecutive in nature.
In fact, the neuropsychological profile found in patients with Parkinson’s disease resembles that seen in patients with frontal lobe damage.
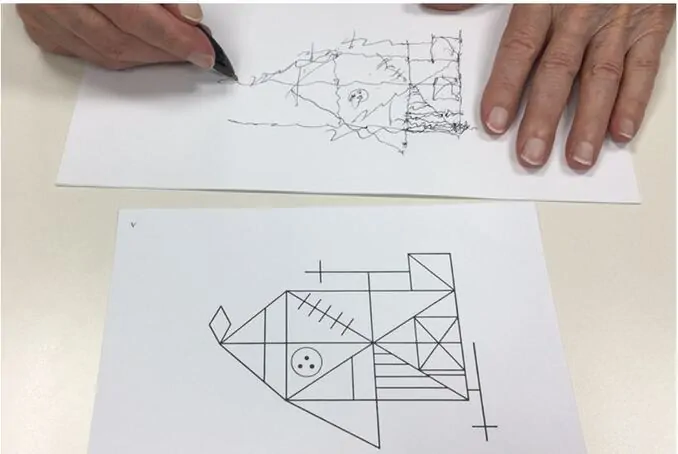
However, we can also find patients who have clinical complaints from the early stages, such as difficulty sustaining attention while reading, during prolonged mental effort, or when performing certain mental operations.
Difficulty “finding the word” (the “tip-of-the-tongue phenomenon”) is characteristic and is related to deficits in semantic verbal fluency from very early stages.
Problems recalling recent episodic events are also common and are related to impaired performance on free-recall verbal memory tests and visual memory tests.
Difficulties multitasking, planning activities, and organizing daily life (mail, finances, work projects) may be noticed very early by patients and have been linked to executive dysfunction.
Despite the early appearance of visual perception deficits, patients don’t usually report complaints about motion perception or visual recognition.
As cognitive impairment progresses, symptoms related to memory and executive functions become more evident to both the patient and those around them.
Problems in the transition to dementia
In the transition to dementia, language problems arise: patients with Parkinson’s disease have trouble understanding and producing language and tend to lose the thread of the conversation.
Language problems in the middle and advanced stages are characterized by impaired sentence comprehension, poor verbal output, and reduced semantic activation.
Therefore, systems other than the dopaminergic system and circuits other than the frontostriatal circuits must necessarily be affected in Parkinson’s disease. There is growing evidence that cholinergic system involvement is crucial in the cognitive disorder associated with Parkinson’s disease.
Neuropsychological rehabilitation in Parkinson’s disease
Some trials have studied the benefits of cholinesterase inhibitors on cognition, behavior, and quality of life in patients with Parkinson’s disease and dementia, but no drug approach specifically aimed at treating mild cognitive impairment in these patients or preventing the progression of symptoms has yet been approved.
However, although the evidence is still limited, improvement in cognition has also been observed in patients with Parkinson’s disease through non-drug interventions.
Cognitive behavioral therapy has proven remarkably effective as a treatment for depression and anxiety in these patients, improving their ability to cope with the disease and their quality of life.
But what is increasingly becoming established as a key strategy to delay decline toward stages close to dementia in Parkinson’s disease is cognitive training, physical exercise, or a combination of both.
Cognitive training has been shown to be safe and to produce a measurable improvement in cognitive performance, particularly in working memory and executive functions, mainly in information processing speed.
The evidence supports everything from stimulation through paper-and-pencil tasks to strategies based on computerized programs.
Benefits have also been observed both with general training and with training focused on specific cognitive processes (mainly executive functions), as well as with exercises controlled through movement.

Working with video games or virtual reality also becomes skills training that is often perceived as enjoyable, engaging motivational and emotional aspects (remember the weight of apathy), increasing engagement with rehabilitation and, as a result, the patient’s long-term commitment to the work.
The competitive element can be an additional motivating factor for staying involved in the cognitive training program, with an impact on social and family aspects.
More frequent training
Another advantage is that these tools allow the work to be done at home (always with a professional’s supervision and monitoring), which increases training frequency.
We should also add that, when analyzing the specific characteristics of the disease, with its areas and functions affected to a greater or lesser extent in each case, programs designed for patients with focal lesions that have proven effective can also be beneficial for patients with Parkinson’s disease in slowing decline. This translates into better participation in society and better quality of life.
Despite the progress made in developing cognitive training for these patients, we must be aware that this work aims to reduce the burden of symptoms and to improve functionality and quality of life.
We must not forget that, because it is a neurodegenerative disease, the complete disappearance of symptoms is out of reach, since the progression of the disease is currently inevitable.
Conclusion
In conclusion, cognitive training combined with behavioral interventions can help patients with Parkinson’s overcome the enormous challenge of living with this disease. Our goal as professionals or family members should always be to maximize their well-being and quality of life.
Although research into the real benefits of these non-drug strategies is still in its early stages, and methodological limitations are in many cases practically insurmountable because of the complexity of this disease, working to optimize these strategies so that they are effective for patients, in both the early and advanced stages of the disease, is a huge challenge that should encourage us to keep working in this direction.
References
- Troster, A. I. [Ed]. (2015). Clinical neuropsychology and cognitive neurology of Parkinson’s disease and other movement disorders. Clinical Neuropsychology and Cognitive Neurology of Parkinson’s Disease and Other Movement Disorders.New York, NY, US: Oxford University Press.
- Wilson, B. A., Winegardner, J., van Heugten, C. M., &Ownsworth, T. (2017). Neuropsychological Rehabilitation: The International Handbook. Taylor & Francis.
- Fernández de Bobadilla, R. (2017). Desarrollo y validación de nuevas herramientas para la valoración cognitiva y funcional del deterioro cognitivo leve en la enfermedad de Parkinson. Doctoral thesis. Universidad Autónoma de Barcelona.
If you’re a neuropsychologist or occupational therapist and want to work on the main cognitive processes affected in people with Parkinson’s, don’t miss this article with cognitive stimulation exercises for people with this disease:
10 cognitive stimulation exercises for Parkinson’s disease
En este artículo te proponemos 10 ejercicios de estimulación cognitiva para la enfermedad de Parkinson. Están dirigidos a que los profesionales de la rehabilitación y estimulación cognitiva los trabajen con sus pacientes en terapia.
“This article has been translated. Link to the original article in Spanish:”
Rehabilitación neuropsicológica en la enfermedad de Parkinson

 Chiari I Malformation. A Clinical Case

Leave a Reply